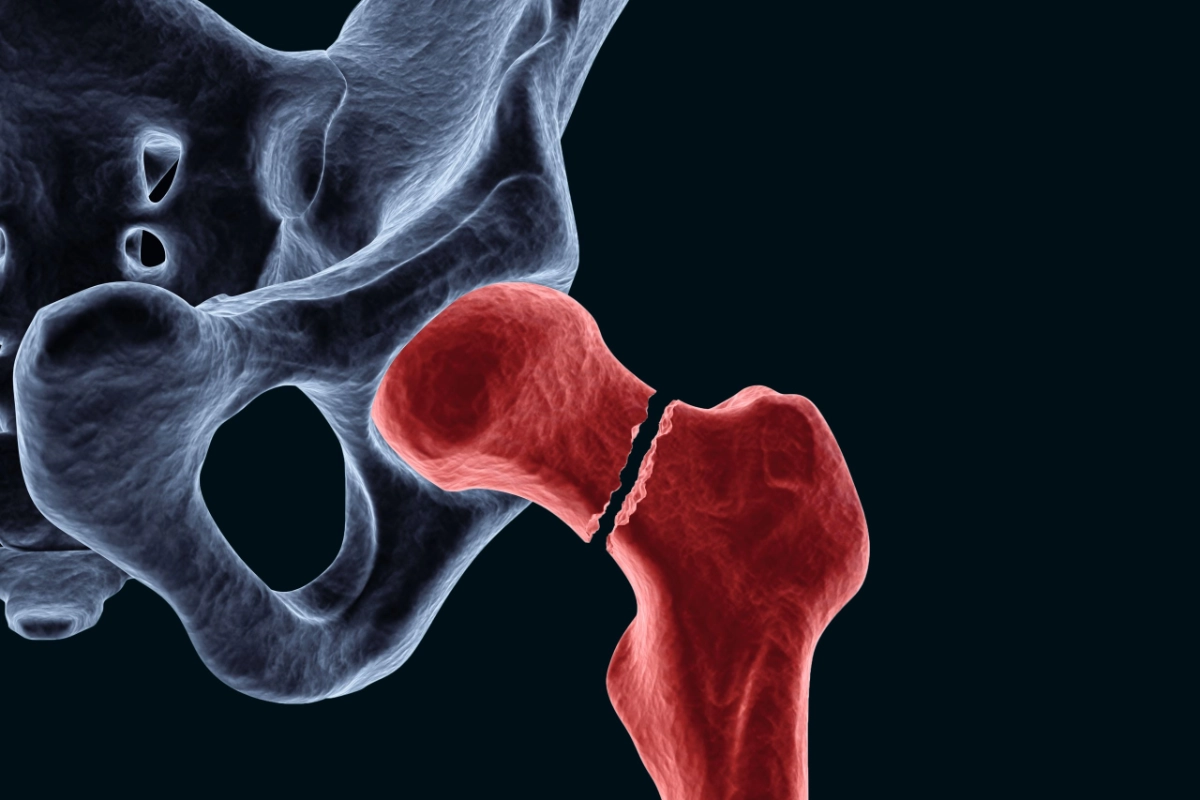
Fractured Neck of Femur (FNOF)
Hip fractures are a common occurrence worldwide, with both a significant impact on the affected individuals as well as the healthcare system. The consequences of hip fractures can be severe, leading to decreased mobility, increased risk of complications, and a lower quality of life.1-3
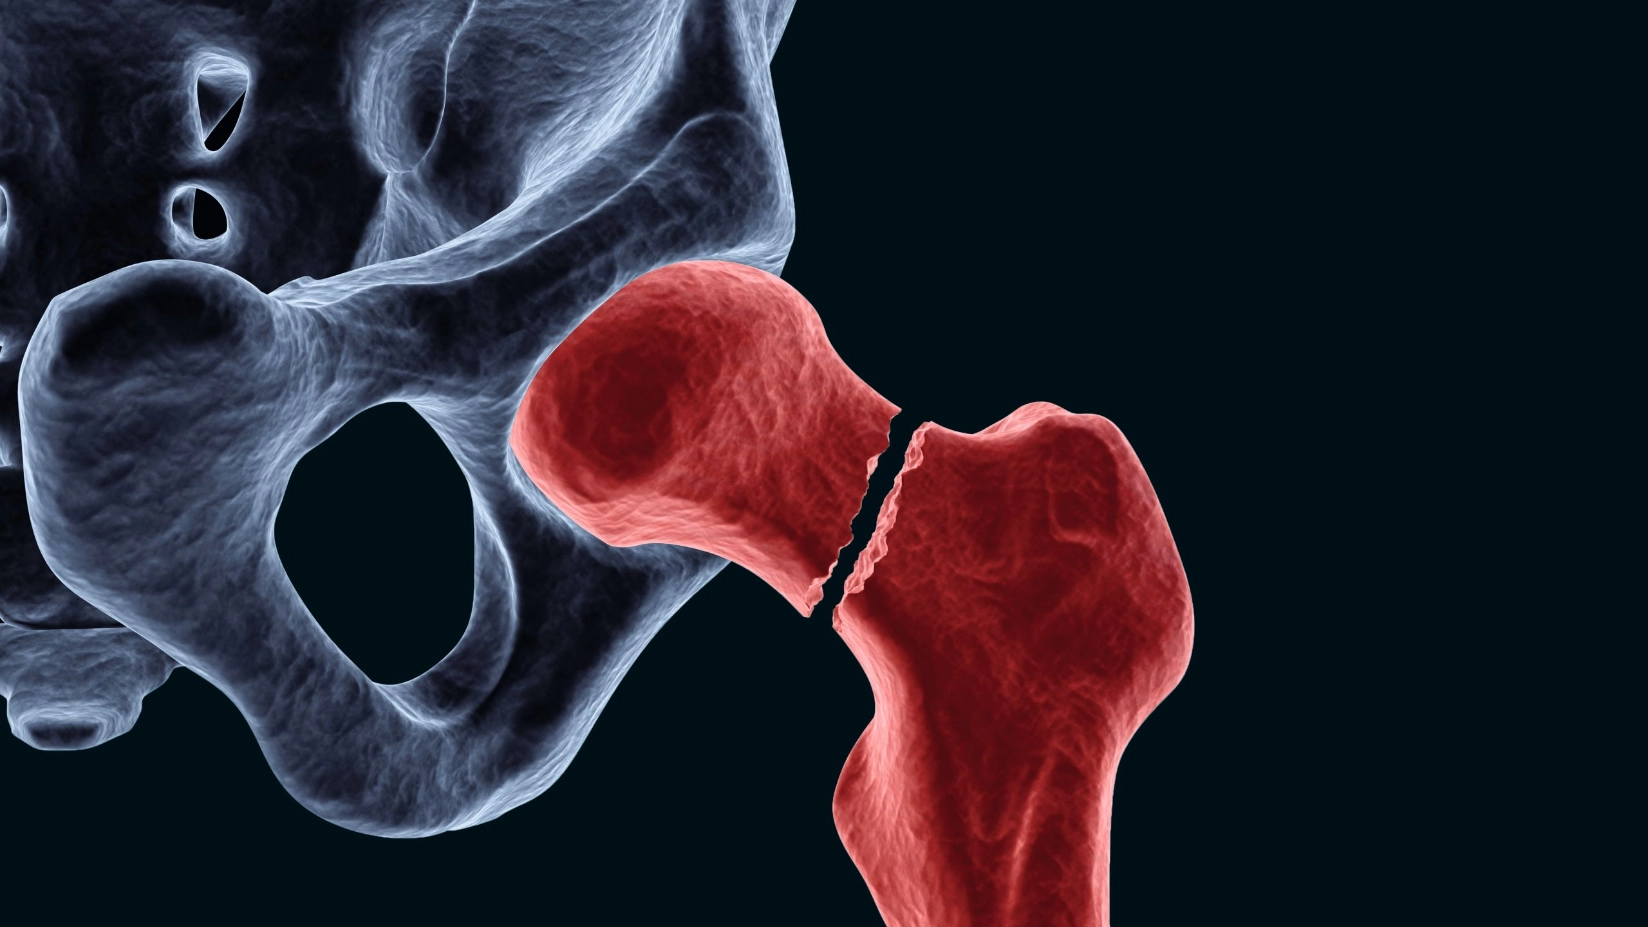
Hip fractures, particularly fractured neck of femur (FNOF), affect individuals of all age groups, however they are more common in the elderly population. This is generally due to low-energy falls and is therefore often associated with osteoporosis.1,4 Proximal femur fractures generally require hospitalisation and surgical treatment, frequently leading to disability and being associated with high morbidity and mortality.1,3,5
The treatment of FNOF with a hemiarthroplasty is considered an option for less fit and less mobile patients with lower life expectancy. Advantages of hemiarthroplasty include a short operation time and quick mobilisation of the patient associated with acceptable clinical, functional, and radiological outcomes.6
Cemented Hemiarthroplasty after FNOF
Hemiarthroplasty can be performed using either cemented or uncemented prostheses. Cemented hemiarthroplasty involves the use of bone cement to secure the prosthesis and has been shown to offer several advantages over uncemented hemiarthroplasty in older patients. It is associated with fewer complications, including less intraoperative and periprosthetic fractures, as well as a lower amount of dislocations or infections, thus leading to a reduced risk of revision compared to uncemented hemiarthroplasty.7-9
Furthermore, patients undergoing cemented hemiarthroplasty experience better mobility within the first year of surgery, along with a modest but significant improvement in quality of life.9,10
Therefore, national guidelines recommend the use of cemented femoral stems for the arthroplastic management of hip fractures.11,12
Dual Antibiotic-Loaded Bone Cement Reduces Risk for Infection in Hemiarthroplasty after FNOF13-16
Periprosthetic joint infection (PJI) remains one of the most prevalent complications among FNOF in hemiarthroplasty. The occurrence of PJI in FNOF patients is much more frequent and even more devastating than in patients undergoing elective hip replacement.17
The use of antibiotic-loaded bone cement (ALBC) covers one significant aspect of local infection prevention among others.
A meta-analysis from 2025 compared dual antibiotic-loaded bone cement (DALBC) with single antibiotic-loaded bone cement (SALBC) in patients undergoing hemiarthroplasty after FNOF. The meta-analysis included five studies comprising a total of 28,418 patients.18
Data from four studies were pooled for the outcome of ‘deep surgical site infection’; in this analysis, DALBC was associated with a 53% relative risk reduction (relative risk (RR) 0.47; p = 0.002).18 Across the four studies, the use of DALBC reduced the risk for infection to similar levels ranging between 1.1% - 1.2%, while reported infection rates ranged between 1.7% - 3.5% with SALBC.13-16
Thus, the use of a DALBC such as COPAL® G+C can effectively lower the risk of PJI and its sequelae in higher risk patients.
PJI rate in % according to bone cement use
| Sprowson et al. 2016 | Tyas et al. 2018 | Savage et al. 2019 | Agni et al. 2023 |
|---|---|---|---|
| n = 848 | n = 1.941 | n = 206* | n = 4.936 |
| 12 months Follow-up | n.a. | 12 months Follow-up | 90 days Follow-up |
* including 26 total hip arthroplasty cases
Beyond Femoral Neck Fracture: Hip Replacement in Older Patients
Hip arthroplasty following FNOF is an important part of hip replacement care in older patients. In addition, arthroplasty care for older patients includes revision procedures and elective procedures for degenerative conditions. In Germany in 2024, patients aged 75 years and older accounted for 38.9% of primary hip procedures and 52.1% of revision procedures.19 This highlights the importance of hip arthroplasty in the elderly.
Multimorbidity and reduced regenerative capacity in older patients pose particular challenges for individualized risk assessment and treatment planning.17,20 The risks of periprosthetic fracture and infection, as well as the potential need for revision surgery, should also be considered. 8,9 An evidence-based treatment strategy tailored to the individual patient is therefore particularly important.
Read our article to learn more about the key challenges in hip replacement in older patients and potential approaches to improving treatment outcomes.